Transhumeral amputation can profoundly impair upper-extremity function and quality of life, particularly in patients who are unable to tolerate a conventional socket prosthesis. Although socket-based prosthetic management remains the standard of care, some patients experience persistent soft tissue irritation, pain, and discomfort, as well as mechanical limitations that restrict functional use, including shoulder range of motion. Osseointegration offers an alternative method of prosthetic attachment by securing the prosthesis directly to the skeleton, eliminating the socket interface and improving suspension, comfort, control, and range of motion in appropriately selected patients.
The Osseointegrated Prostheses for the Rehabilitation of Amputees (OPRA) Implant System uses a staged surgical approach to establish direct skeletal attachment of a prosthesis to the residual humerus. Adjunctive procedures such as targeted muscle reinnervation (TMR) may be performed concurrently to optimize peripheral nerve management, reduce neuroma-related pain, and improve myoelectric prosthetic control.
Here we present the case of a patient who sustained a traumatic right transhumeral amputation following a motorcycle accident and underwent staged transhumeral osseointegration using the OPRA system with concurrent TMR.
Case Highlights:
- A 30-year-old male with a traumatic right transhumeral amputation had persistent difficulty using a conventional socket prosthesis due to residual limb soft tissue compromise.
- Stage I osseointegration included revision of the transhumeral amputation, intramedullary OPRA fixture placement, and TMR.
- Stage II established the skin-implant interface and placed the transcutaneous abutment.
- Prosthetic rehabilitation was uncomplicated, and the patient returned to independent activities of daily living and work as a tattoo artist.
Case Presentation
The patient is a 30-year-old male who sustained a traumatic right transhumeral amputation in a motorcycle collision. After recovering from his initial injuries, he pursued prosthetic rehabilitation but continued to have substantial difficulty with a conventional socket prosthesis because of residual limb soft tissue compromise.
Physical examination demonstrated extensive adherent skin grafting over the distal residual limb, although shoulder range of motion was preserved. He continued to experience phantom limb pain, which was managed medically.
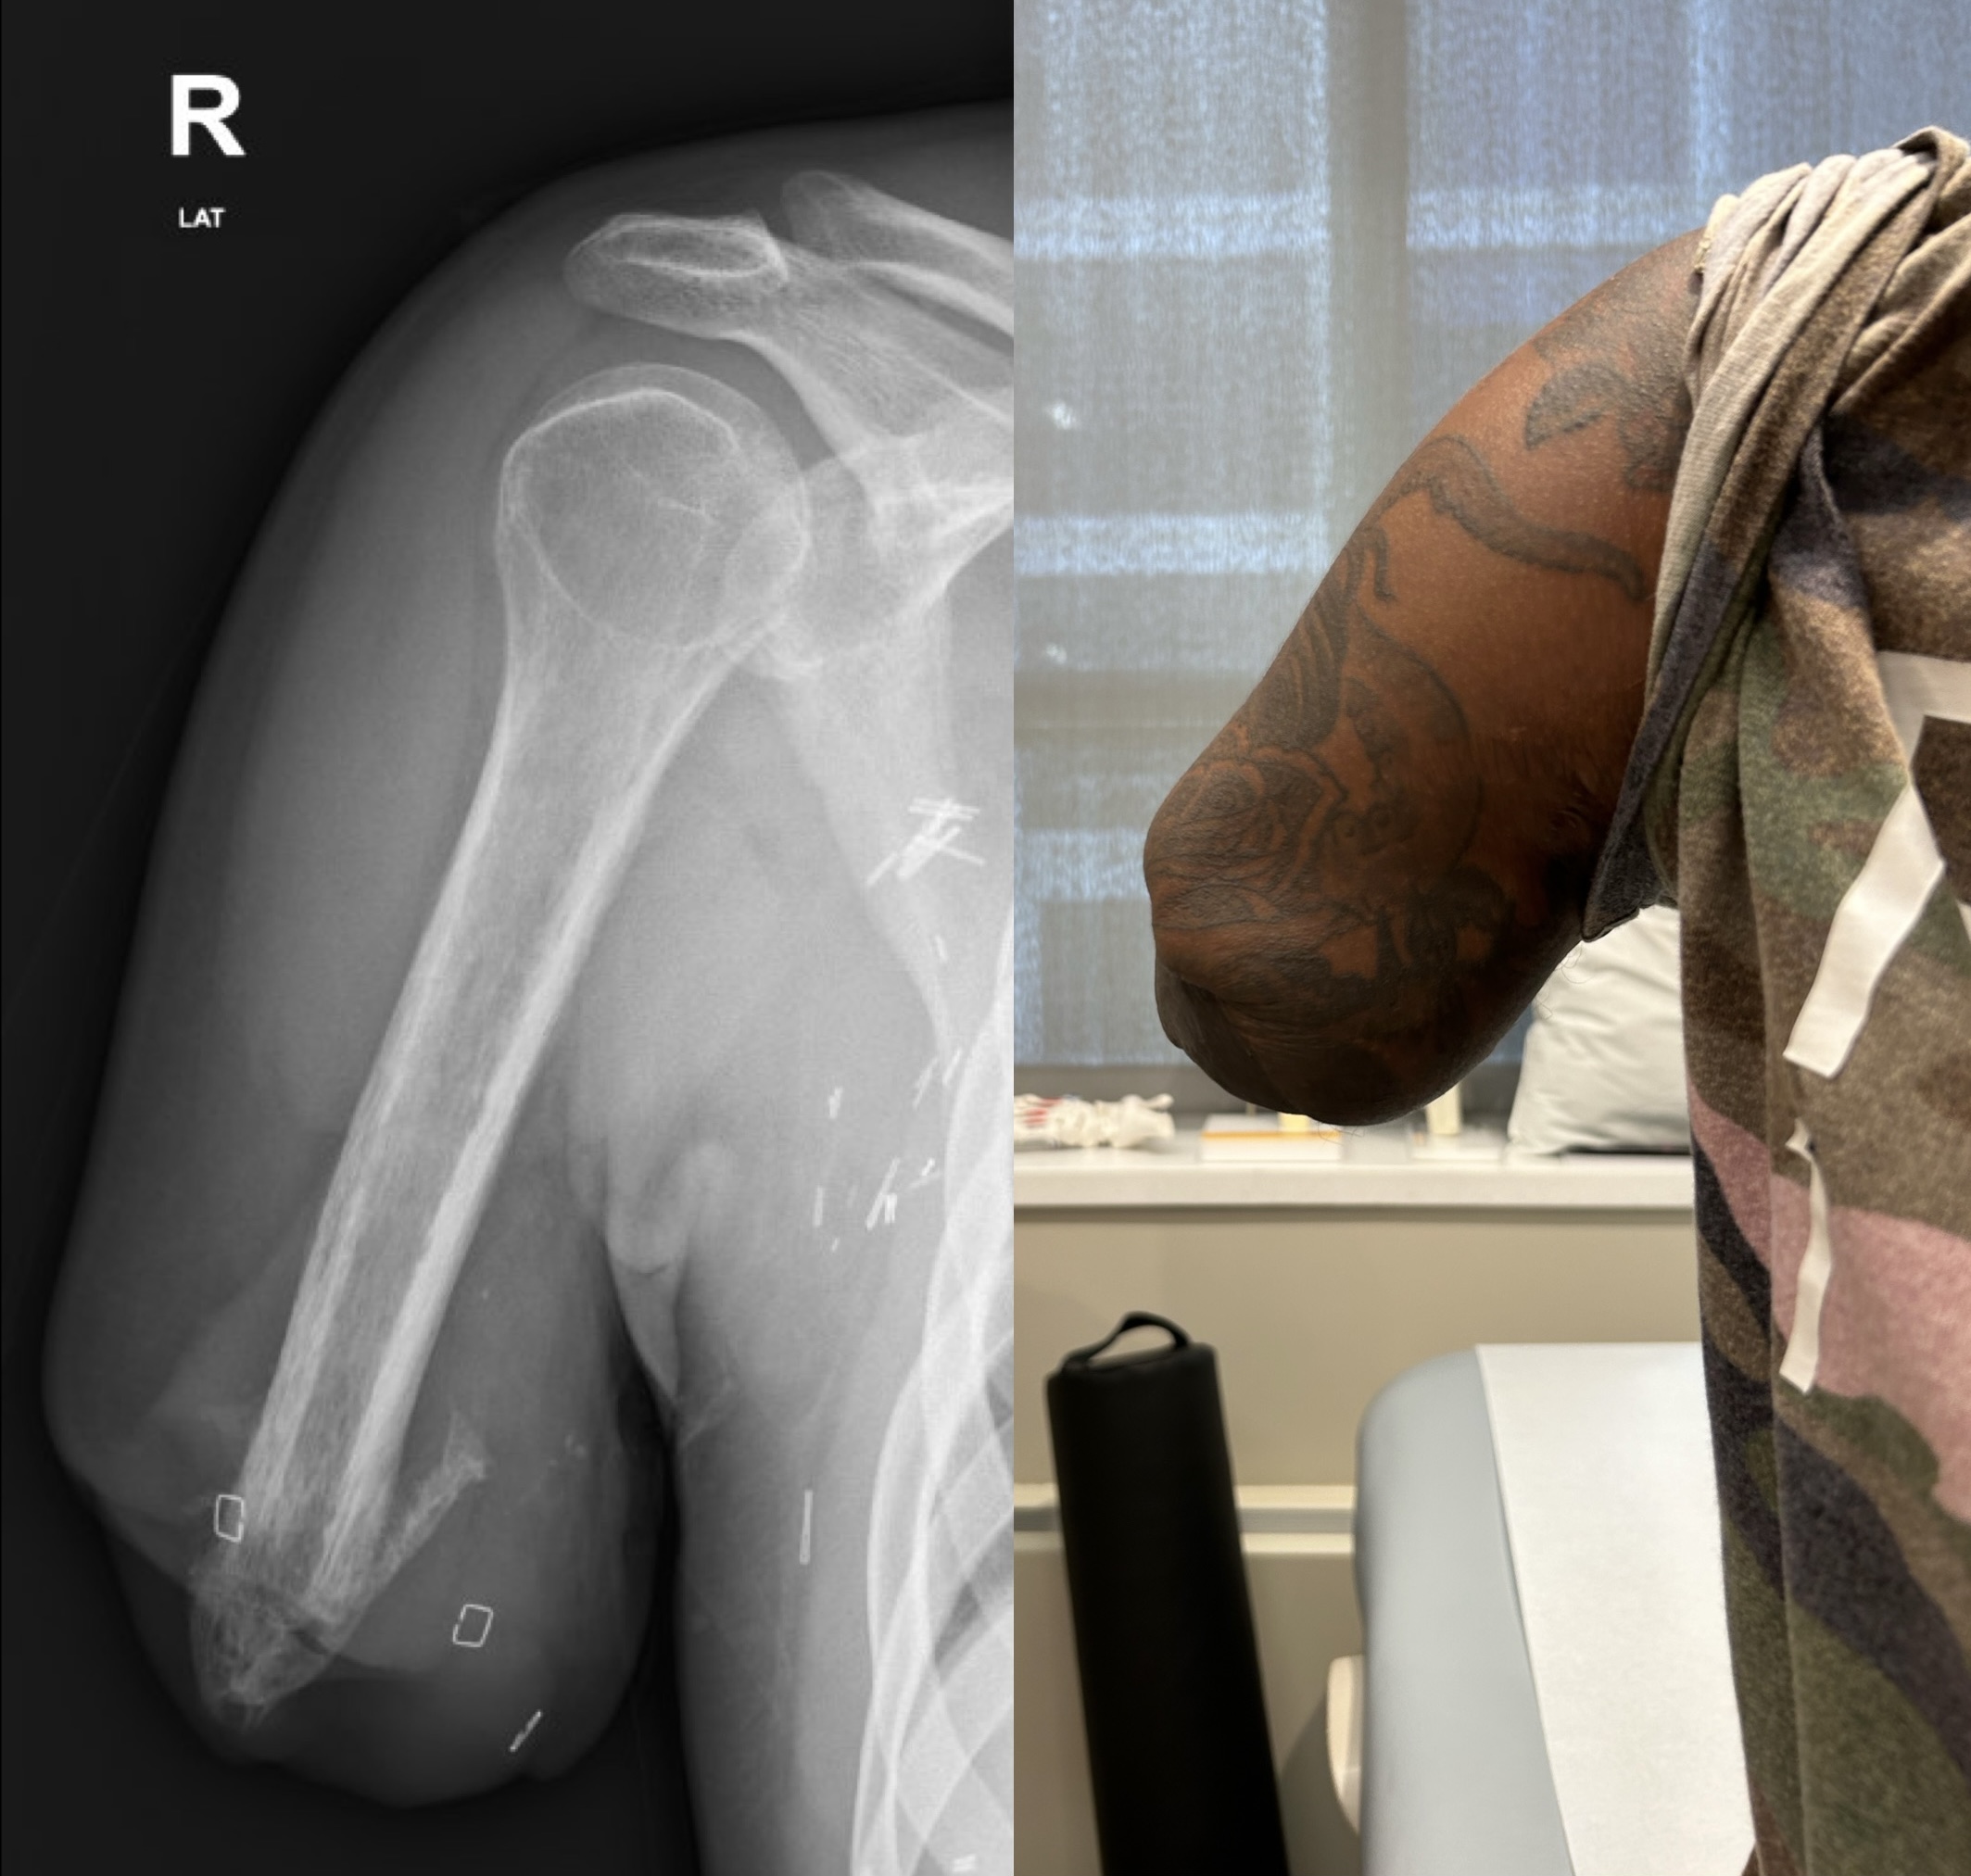
Preoperative radiographs demonstrated a midshaft transhumeral amputation without evidence of infection and with adequate residual humeral bone stock for implant fixation (Figure 1). Given his residual limb anatomy, poor socket tolerance, and functional limitations, he was considered an appropriate candidate for staged transhumeral osseointegration. His full shoulder range of motion also supported his candidacy for osseointegration, as the impant would not restrict his exisiting range of motion.
Operative Management
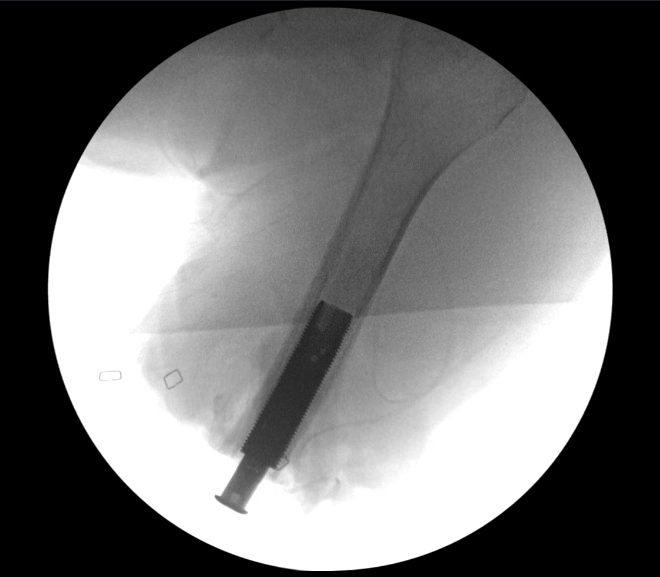
Stage I surgery consisted of revision of the transhumeral amputation and placement of the intramedullary OPRA fixture. Concurrent TMR was performed for peripheral nerve management and to facilitate future myoelectric prosthetic control. The residual humerus was then prepared under fluoroscopic guidance before implantation of the fixture (Figure 2).
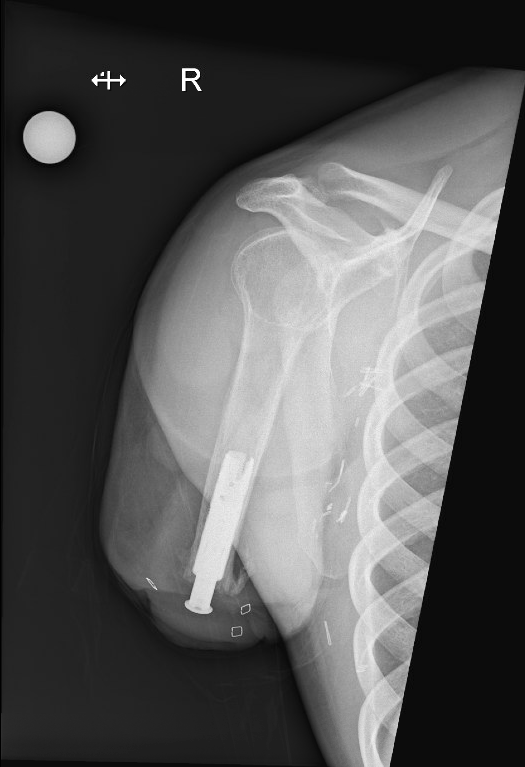
Autologous bone graft was placed around the distal implant, and the residual musculature was reconstructed to establish a stable soft tissue envelope before layered closure. Interval radiographs demonstrated stable position of the intramedullary fixture within the residual humerus (Figure 3).
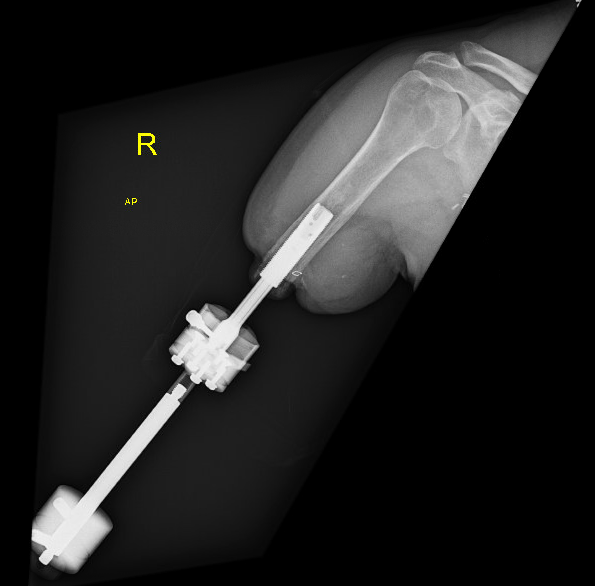
Following successful osseointegration, the patient underwent the second-stage procedure for placement of the transcutaneous abutment. Residual limb revision and soft tissue reconstruction were performed to establish a stable skin-implant interface before placement of the transcutaneous abutment. Intraoperative photographs and video demonstrate creation of the skin-implant interface and placement of the transcutaneous abutment (Video 1).
Final postoperative radiographs confirmed appropriate implant alignment and fixation (Figure 4).
Postoperative Course
The patient progressed through the standard staged rehabilitation protocol without implant-related complications. After soft tissue healing and progressive weight-loading, he began prosthetic rehabilitation with an externally powered upper-extremity prosthesis. Early follow-up demonstrated functional prosthetic use, including active finger motion with a prior prosthetic configuration in November 2025 (Video 2).
At subsequent follow-up, he transitioned to a more advanced externally powered transhumeral prosthesis incorporating an Espire Pro elbow, Motion Control electric wrist rotator, and Zeus S hand. By April 2026, follow-up demonstrated improved prosthetic function, including active elbow motion and finger control with the updated configuration (Video 3).
He reported daily prosthesis use and utilized the device for activities of daily living, including driving (Figure 5), occupational tasks, and tattooing.

Compared with prior socket-based prosthetic management, he experienced meaningful improvements in comfort and function. The residual limb remained well healed, and chronic residual limb pain was generally well controlled. Minor mechanical issues involving the prosthetic hand components were successfully managed with routine adjustments.
At latest follow-up, he had successfully returned to work as a tattoo artist and continued to demonstrate excellent functional use of the prosthesis (Figure 6).

Discussion
Transhumeral osseointegration offers an important reconstructive option for patients who are unable to tolerate a conventional socket prosthesis. By establishing direct skeletal fixation, osseointegration eliminates many socket-related limitations while improving prosthetic suspension, comfort, and functional use. In selected patients, concurrent TMR may further improve outcomes by addressing nerve-related pain and enhancing the potential for advanced myoelectric prosthetic control.
Successful outcomes require careful patient selection, meticulous surgical technique, and coordinated multidisciplinary rehabilitation. Careful residual limb preparation, preservation of a durable soft tissue envelope, establishment of a stable skin-implant interface, and appropriate peripheral nerve management are critical to minimizing complications and optimizing long-term prosthetic function. In this case, extensive residual limb soft tissue compromise and persistent difficulty with socket prosthetic use made the patient an appropriate candidate for staged transhumeral osseointegration.
At latest follow-up, the patient demonstrated durable functional improvement with consistent prosthesis use and successful return to independent daily activities and employment. This case demonstrates the potential for direct skeletal prosthetic attachment to restore function and improve quality of life in appropriately selected patients with transhumeral amputation.